CFM Resolution 2.454/2026 has been in force since August 26. The question is being able to prove that the AI was used correctly.
An auditable record of AI use, demonstrable clinical supervision and preserved medical authorship are not solved with internal policy. They require evidence produced inside the operational workflow. These six playbooks show how to implement this using the RIS, the PACS and the reporting platform you already run.
You are timing the wrong part of the journey.
The board report shows the radiologist's time. The patient feels the entire journey, and almost all of it is waiting that nobody times.
Pressuring the only block you measure shifts risk to review and communication; it does not shorten the wait.
Without a clock per stage, every TAT discussion ends in opinions about who is falling behind.
The last block is the one that most often disappears from dashboards, and the only one where delay turns into harm to the patient.
Structural diagram: the proportions are illustrative, not a measurement. Playbook 01 shows how to instrument each stage with the events your RIS and your PACS already record.
Where can your service already demonstrate compliance, and where does it only have intent?
Each question corresponds to a playbook. Answering is optional and nothing leaves this page before you fill in the form.
Do we know the time of each stage of the exam, not just the total?
Operations and TATDoes every critical finding have a recorded acceptance from an accountable person?
Quality and safetyCan we retrieve which AI version operated on a specific exam?
Governance and LGPDIs there a written map of identifiers and states across PACS, RIS and platform?
InteroperabilityDo our pilots have a decision criterion defined before they start?
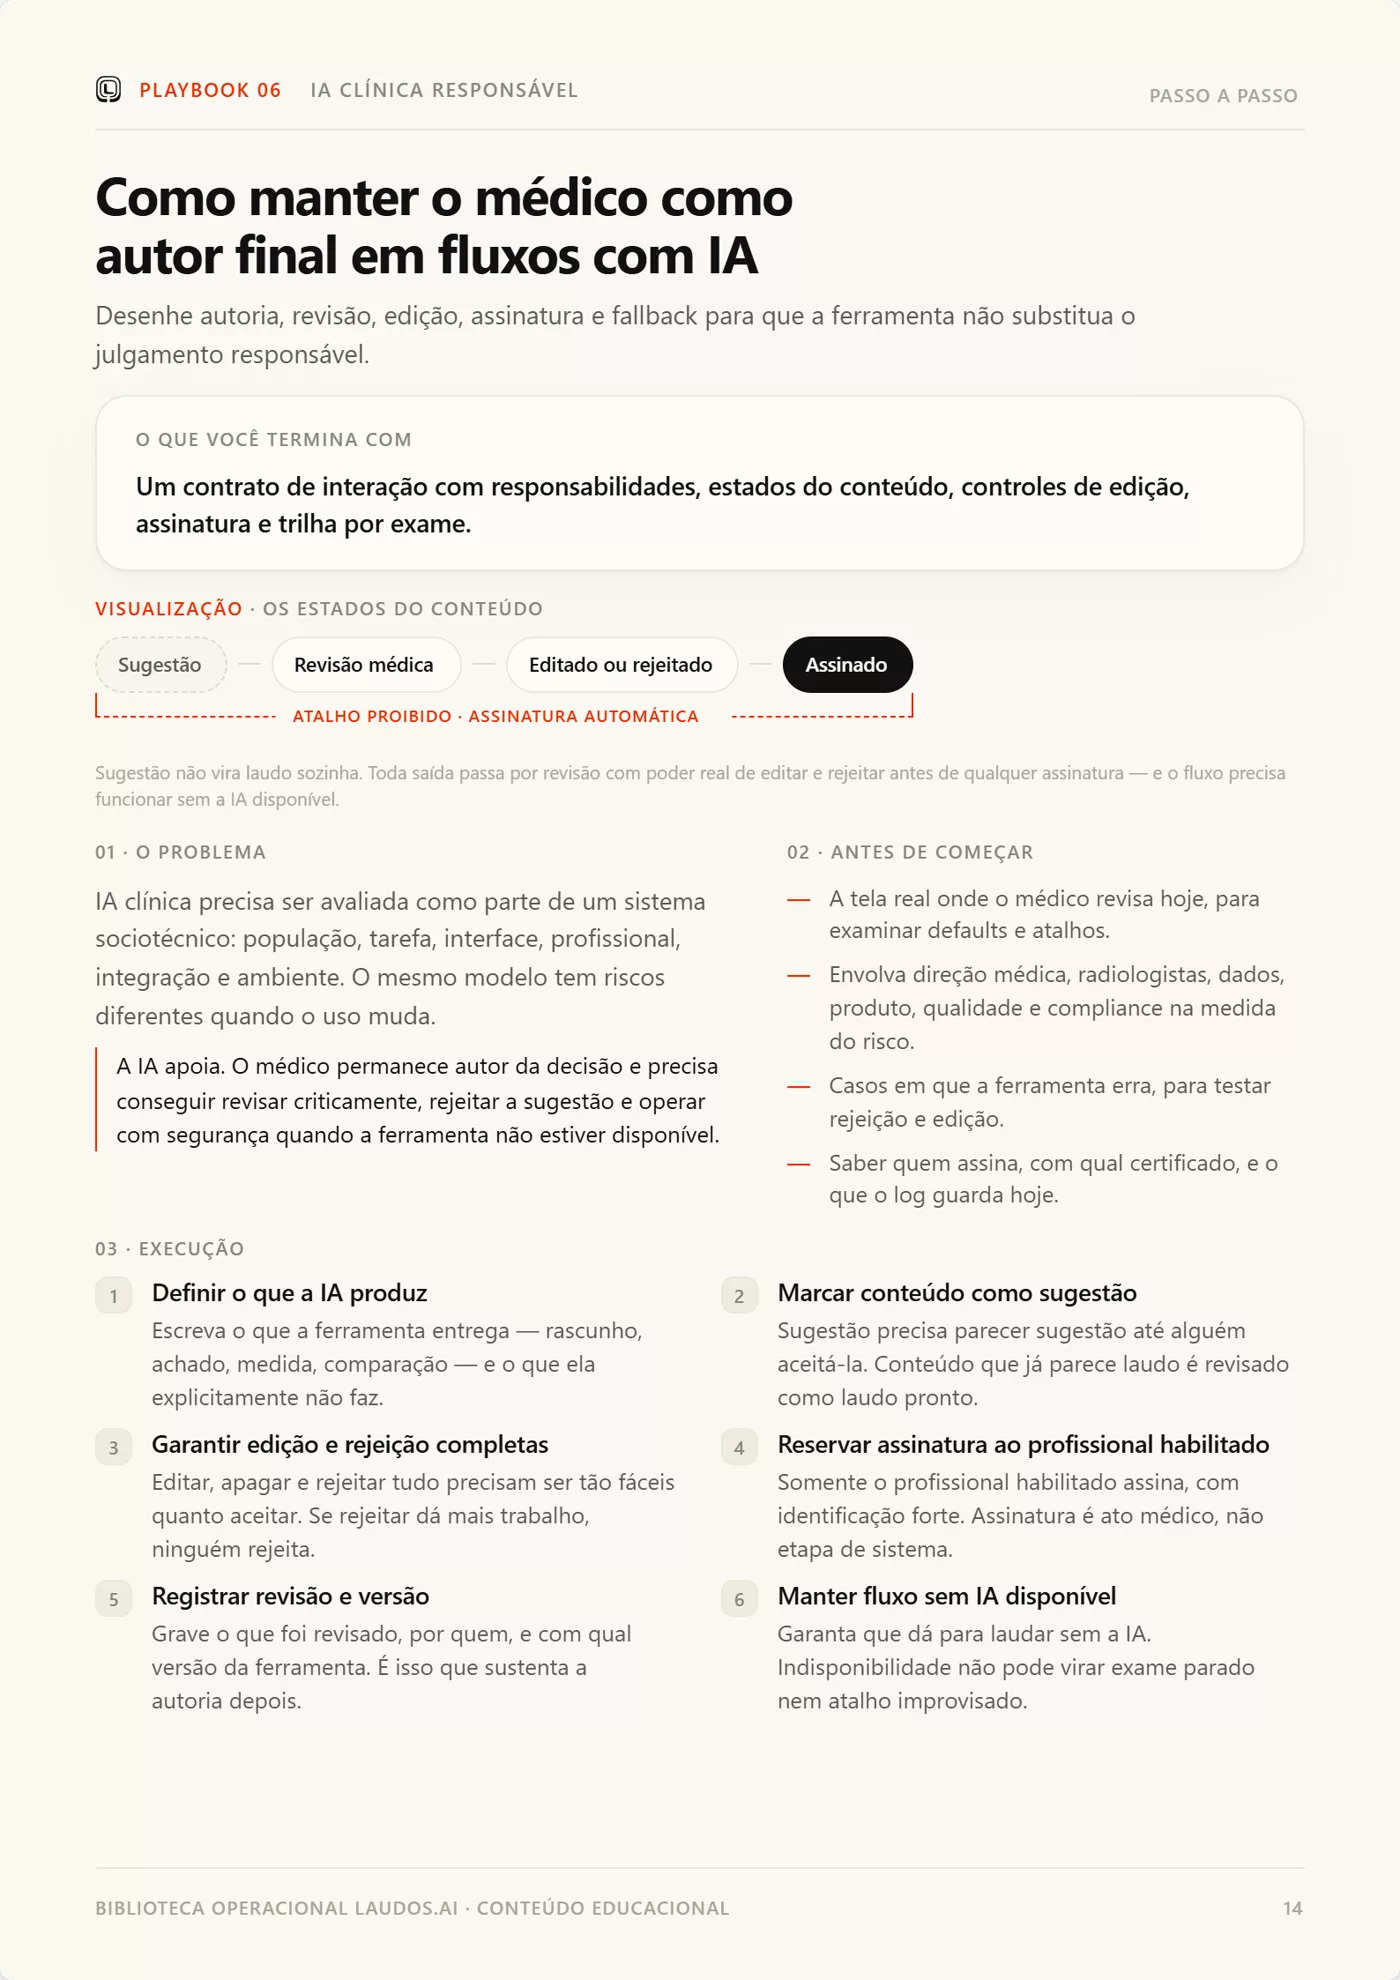
Deployment and adoptionDoes the workflow stay safe when the AI tool becomes unavailable?
Responsible clinical AIAnswer all six to see the map.
Each playbook was designed to move off the page and into operations.
Each one delivers the workflow, the owners, the indicators, the exceptions, the checklist and the decision criteria. Material for implementation, not for presentation.
A suggestion does not become a report on its own. Review must have real power to edit and reject before any signature.
In an audit, "sent" does not prove communication. What counts is evidence of receipt and the response time of an identified accountable person.
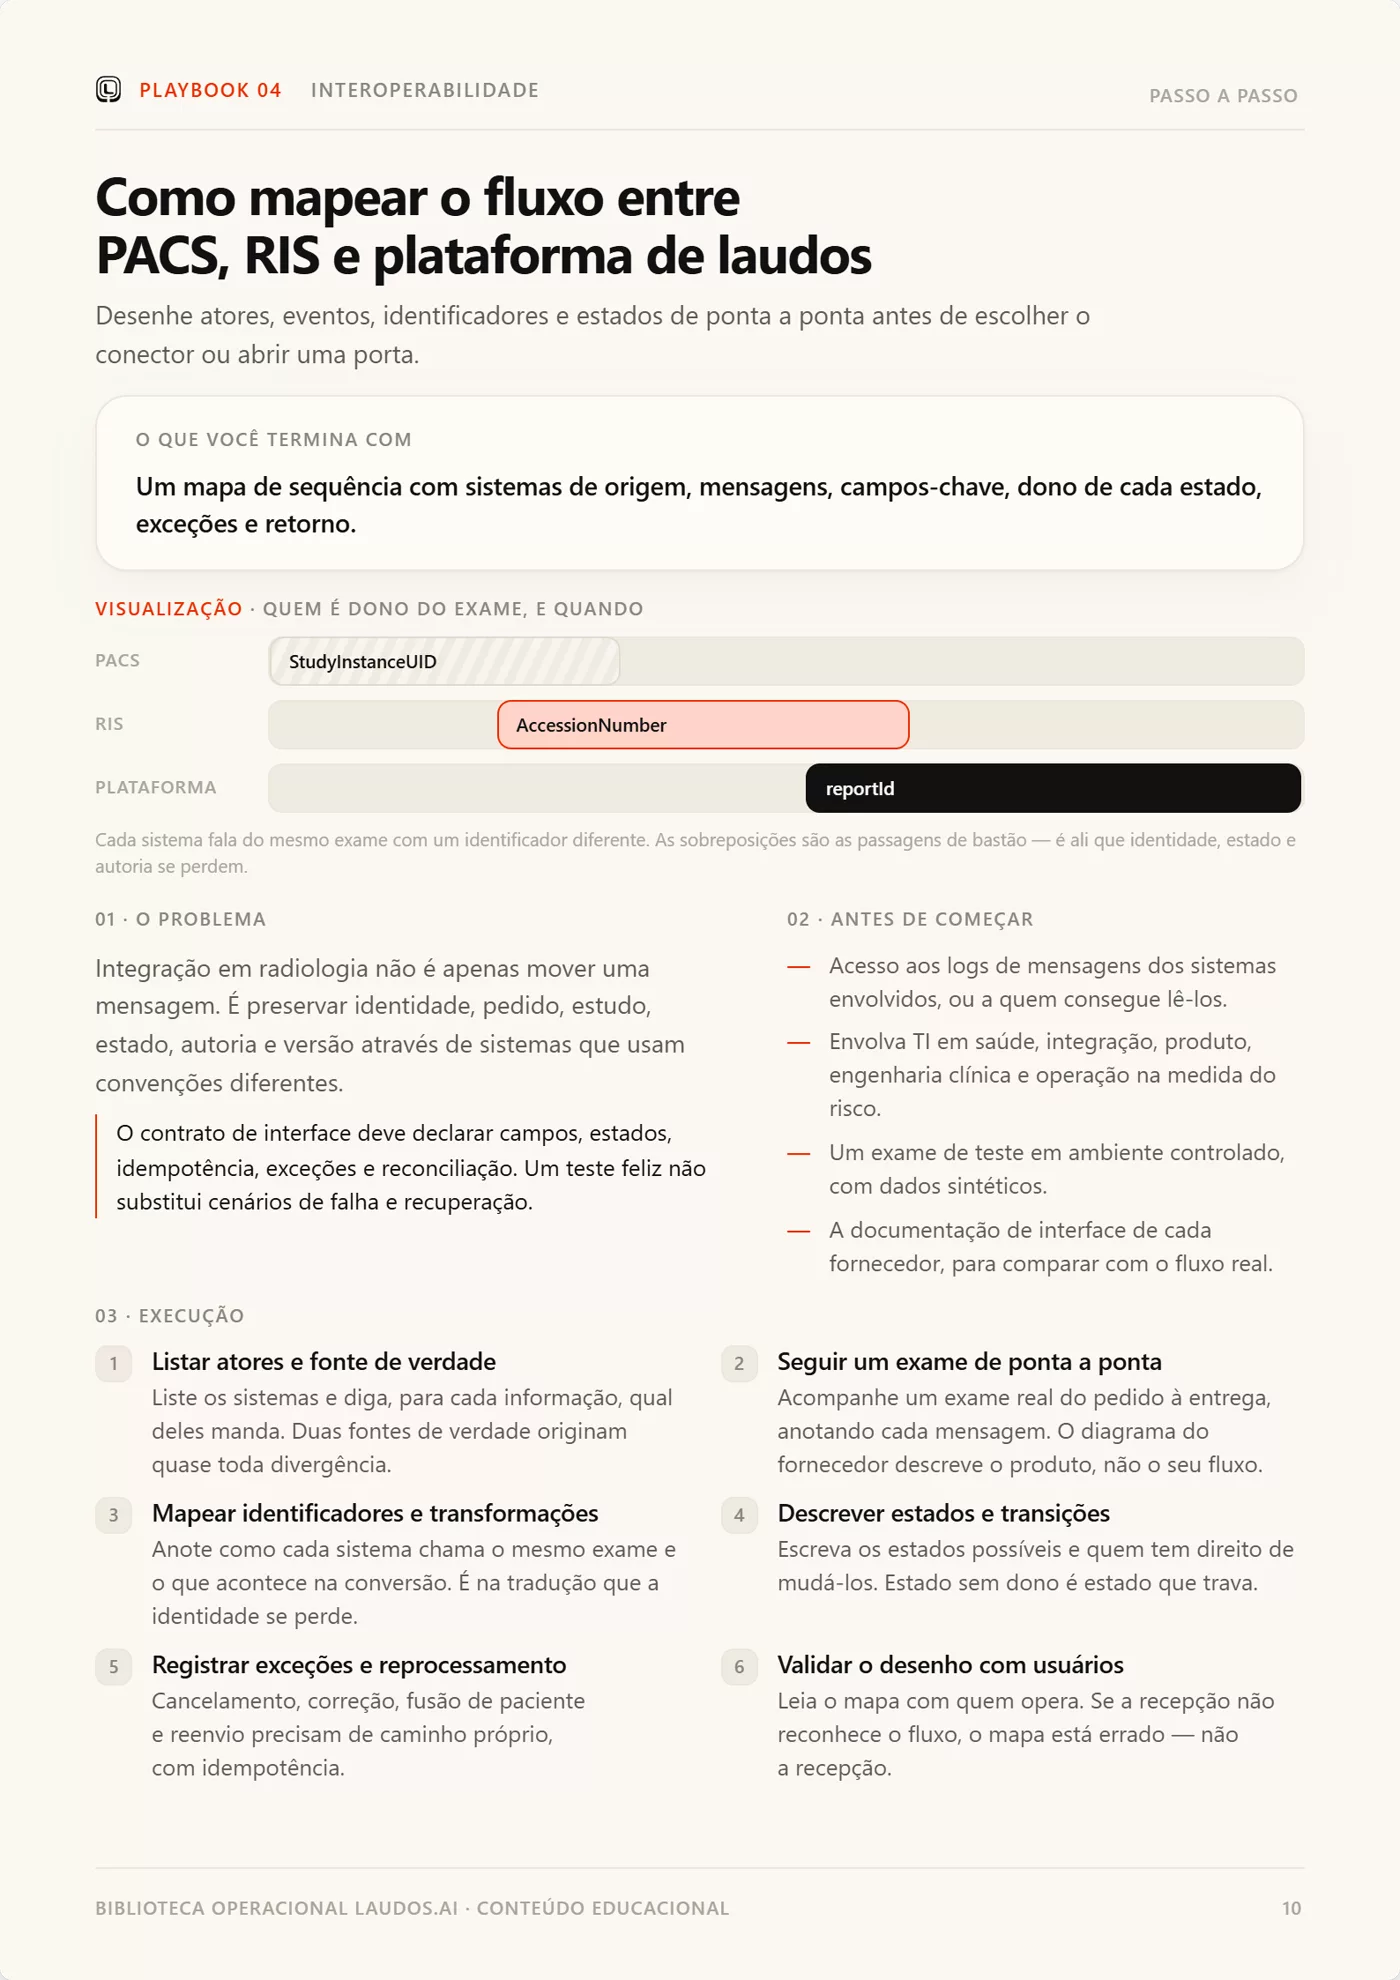
Every regulatory requirement must produce retrievable evidence.
In an audit, intent is not enough. You have to demonstrate how the AI took part in the clinical decision, who supervised and who took on authorship of the report.
Purpose, system, version, operator, output and physician review, retrievable in an audit, without bloating the medical record. Playbook 03.
Context, time, competence and authority to accept, change or reject the suggestion. Playbooks 03 and 06.
Authorship, editing, rejection, signature and a safe workflow when the tool goes down. Playbook 06.
Every statement has a primary source, with issuing body and year.
There is no universal TAT target in these playbooks. Modality, population, data coverage and integration maturity change the result, so the material delivers the method for measuring your baseline instead of a target borrowed from another service.
Each playbook ends in an artifact with an owner, exceptions and a checklist, made to be circulated, marked up and challenged in writing. Educational material: it does not replace medical judgment, institutional policy or legal analysis.